Introduction
Principles of Treatment
General Measures
Topical therapies
Phototherapy
Systemic non-biological therapies
Biological therapies
Treatment in pregnancy
Psoriasis is a common, chronic, immune-mediated skin disease with characteristic red, scaly plaques caused by the excessive proliferation of skin cells.
There are a number of types of psoriasis, including chronic plaque psoriasis, guttate psoriasis, flexural psoriasis, palmoplantar psoriasis, and nail psoriasis.


Despite recent advances in our understanding of the mechanism of how psoriasis develops, psoriasis may be difficult to treat; there is currently no cure and no single treatment works for everyone.
Several treatments may need to be tried before the most suitable regime is established, and different treatments may need to be used concurrently, or in rotation, for best effect or to minimise side-effects.
Treatment of adults with psoriasis includes:
The choice of treatment depends on several factors including severity (PASI and BSA), type of psoriasis, disease impact (DLQI and CDLQI; also see Psychological effects of psoriasis), patient profile and preferences, comorbidities (eg, psoriatic arthritis), and treatment goals eg, improving nail psoriasis or achieving 90% improvement in PASI score.
More details about each form of psoriasis treatment are found on individual topic pages.
Where possible, minimise factors that aggravate or trigger psoriasis, such as stress, streptococcal infections, and certain medications such as lithium, beta-blockers, terbinafine and antimalarial drugs (see: Drug-induced psoriasis).
Health conditions associated with psoriasis include psoriatic arthritis, sleep disturbance, and depression. Treatment for these may help skin disease.
Due to the association between psoriasis and metabolic syndrome, weight loss, smoking cessation, moderation of alcohol intake, and blood pressure control may also lead to improvements in skin disease.
Sun exposure (heliotherapy) may help to clear psoriasis; in many people, psoriasis improves dramatically during summer months or on sunny holidays.
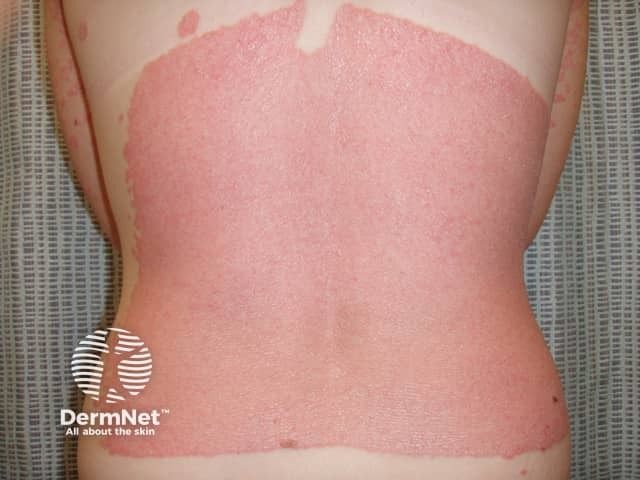


Soaking in warm water can soften the psoriatic plaques and lift the scale.
One avenue of current research is looking at the skin and gut microbiome (the bacteria living on and in the human body) and whether the alteration of this microbiome may be effective in the treatment of psoriasis. To date, probiotics have not been found to help psoriasis.
The regular use of emollients and moisturisers softens psoriasis and adds moisture to the skin. This improves dryness, scaling, and irritation.
Be aware of the flammability of emollients and the risk of slipping in the bath after applying these agents to the feet. Emollients can rarely irritate the skin; this is less likely with ointments than with lotions and creams.
Relatively small, localised patches of psoriasis may improve with hydrocolloid dressing occlusion (eg, using waterproof adhesive dressings).
Keratolytic agents can be useful to reduce the thick scale. They may contain urea (5–40%), salicylic acid (0.5–10%) or propylene glycol (eg, propylene glycol 20% in aqueous cream).
Topical steroids are safe and relatively easy to use for plaque psoriasis, scalp psoriasis, flexural psoriasis, sebopsoriasis, and psoriasis affecting the palms and soles.
Topical steroids are available in various strengths and formulations (including steroid impregnated tape). Topical steroids are also used in combination with other agents, such as with:
Selection depends on the site and type of psoriasis.
Although topical steroids can be useful for the itch, tachyphylaxis can develop with continued use, diminishing the initial anti-inflammatory effect.
Topical steroids can be used under medical supervision during pregnancy and, alongside emollients, are generally the first-line treatment of psoriasis in pregnancy.
Vitamin D-like compounds including calcipotriol, calcitriol, and tacalcitol are applied once or twice daily to reduce the thickness and scale of plaques (redness may persist).
Calcipotriol may be used for chronic plaque psoriasis and scalp psoriasis, whereas calcitriol ointment is often preferred for flexural or genital psoriasis due to lower irritation potential.
When combined with ultraviolet (UV) therapy, calcipotriol should be applied after exposure to UV radiation because UV deactivates calcipotriol and calcipotriol acts as a sunscreen.
Calcipotriol is available in combination with a very potent topical steroid, betamethasone dipropionate, as a gel/ointment or foam. This combination is often the first-line of treatment in plaque psoriasis but should not be used continuously or over large areas due to excessive steroid use risks.
Vitamin D analogues are best avoided in children under 6 years, and during pregnancy and during lactation due to a lack of safety data.
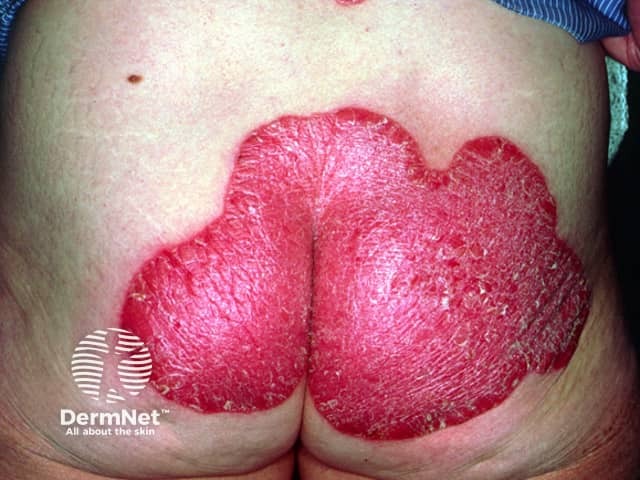
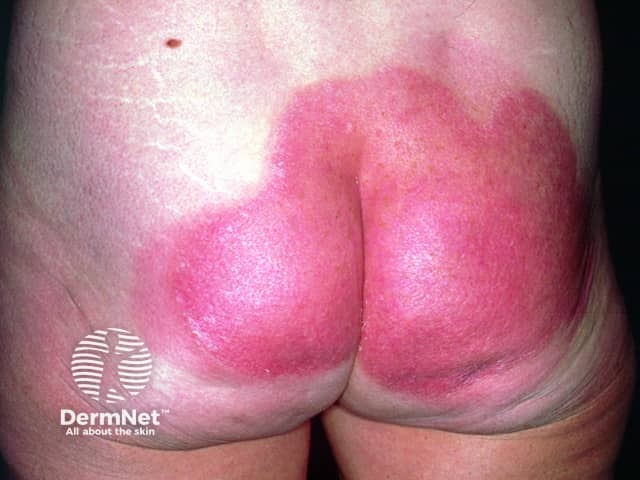
Coal tar is available as solutions, lotions, creams, ointments, gels, and shampoos, often mixed with other ingredients.
Dithranol (also called anthralin or anthralian), is occasionally recommended for chronic plaque psoriasis, it can be very effective but has practical drawbacks.
Application may be considered complex:
Dithranol permanently stains fabrics and temporarily stains the skin.
The calcineurin inhibitors, tacrolimus ointment and pimecrolimus cream, are mostly used to treat atopic dermatitis; their use for psoriasis is off-license. They serve as steroid-sparing agents on sensitive sites where the skin is thinner (eg, the face, flexures, and genital areas) but are not effective for treating chronic plaque psoriasis elsewhere unless under occlusion.
Tazarotene is a topical retinoid, applied once daily to plaque psoriasis as a 0.05% or 0.1% cream. The most common side effect is skin pain and local irritation.
Recent advancements have introduced novel topical therapies with new mechanisms of action, offering promising alternatives.
Tapinarof 1% cream (VTAMA®) is a once-daily, aryl hydrocarbon receptor (AhR) modulating agent approved by the FDA in May 2022 for the treatment of mild to severe plaque psoriasis in adults.
Roflumilast 0.3% cream (Zoryve™) is a once daily, PDE4 inhibitor approved by the FDA in 2022 for the treatment of plaque psoriasis in patients aged 12 years and older. Roflumilast cream has been shown to improve both skin symptoms and itch in psoriasis patients.
Research continues into additional AhR modulators, PDE4 inhibitors, and Janus kinase (JAK) inhibitors as potential topical treatments for psoriasis. These agents target immune-mediated pathways involved in psoriasis while minimising systemic absorption and adverse effects. They include novel drug delivery systems and microbiome-based approaches. These agents include:
Phototherapy involves the use of UV radiation for skin disorders and remains a key treatment for psoriasis, particularly when topical therapies are ineffective or impractical. Traditional phototherapy includes narrowband UVB (NB-UVB) and psoralen plus UVA (PUVA) therapy. However, recent advancements aim to enhance efficacy, minimise risks, and improve accessibility.
NB-UVB (311–312 nm) is effective for chronic plaque and guttate psoriasis, especially during colder months.
PUVA remains useful for thick plaque and palmoplantar psoriasis but carries a higher risk of skin cancer than NB-UVB. Psoralens sensitises the skin to UVA; it may be given either by mouth or by immersion in a bath containing psoralens.
Excimer laser (308 nm UVB) delivers high-dose, focused light to localised psoriatic plaques.
Systemic (oral or injectable) medication may be required to treat psoriasis when:
The selection of the appropriate medication is specific to each individual patient, as each agent carries its own risks and benefits.
As a rule, systemic steroids should be avoided as they can make psoriasis worse or unstable and difficult to control with other treatments.
Most treatment options require regular monitoring including blood tests. See the individual drug page for more information.
Methotrexate is an immunomodulatory and anti-inflammatory treatment used to treat psoriasis, psoriatic arthritis, and Crohn disease.
Ciclosporin is an immunosuppressant used short-term to treat atopic eczema and psoriasis.
Acitretin is a vitamin A-like compound or retinoid that is particularly effective for palmoplantar psoriasis. Women must avoid pregnancy during therapy and for sever years after even short exposure to this drug.
Apremilast is a phosphodiesterase-4 inhibitor used to treat psoriasis and psoriatic arthritis.
Fumaric acid esters are immunosuppressants.
Other non-biological oral medications for psoriasis include:
Biological agents (biologics) are targeted therapies derived from living organisms, including human, plant, animal, or microbial sources. Unlike traditional immunosuppressants that broadly dampen the immune system, biologics work by selectively inhibiting specific cytokine or immune pathways to treat inflammatory disorders and cancers.
Biologics are highly effective for psoriasis when conventional therapies have failed, are contraindicated, or cause intolerable side effects.
Biological agents currently approved for psoriasis target specific immune pathways.
Tumour necrosis factor-alpha (TNFα) inhibitors
Interleukin-12 and Interleukin-23 (IL-12/23) inhibitors
Interleukin-23 (IL-23) inhibitors
Interleukin-17 (IL-17) inhibitors
Biologic agents have also been approved for conditions such as rheumatoid arthritis, psoriatic arthritis, ankylosing spondylitis, Crohn disease, ulcerative colitis, hidradenitis suppurativa, and juvenile idiopathic arthritis.
Older biologics, efalizumab (Raptiva®) and alefacept (Amevive®), were withdrawn due to safety concerns.
Psoriasis is an immune-mediated inflammatory condition involving upregulation of T-cells that result in excessive cytokine release, leading to inflammation, redness, and scaling.
Biologic agents work by inhibiting key cytokines involved in the pathogenesis of psoriasis.
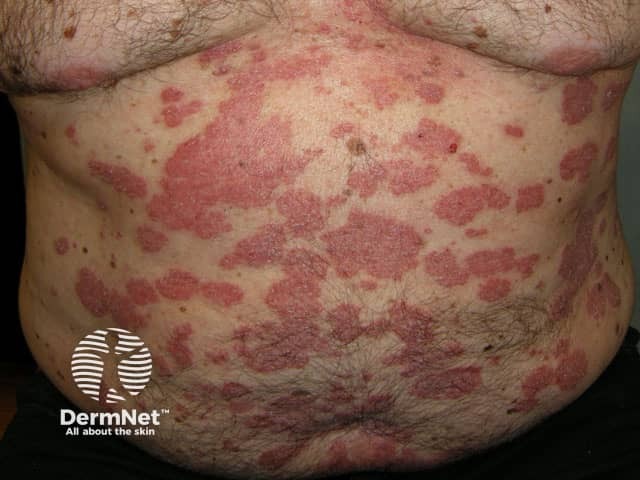
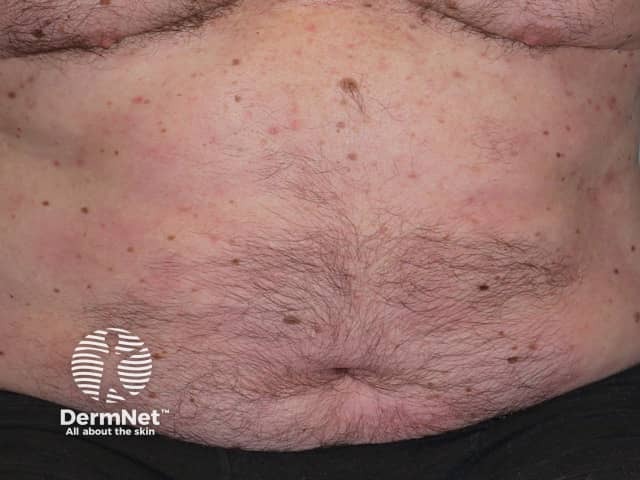
Biologics are typically administered by subcutaneous injection at regular intervals, with the exception of infliximab, which is given intravenously in a healthcare setting.
Typical dosing schedules:
Some patients require combination therapy with conventional systemic medications (eg, methotrexate) to enhance efficacy or reduce the risk of antibody formation.
Biologics are generally well-tolerated but can cause side effects, and require specific screening and routine monitoring. For more information, including information on vaccination and biologic use, see the general page on biologics and/or individual drug pages.
Due to their high cost, biologics are often reserved for patients with moderate-to-severe psoriasis who have failed conventional treatments. Funding and reimbursement policies vary by country.
Biosimilars (nearly identical versions of biologics with reduced costs) are available for infliximab, adalimumab, etanercept, and ustekinumab with more in development.
New or existing biologics are under development or investigation for psoriasis, including:
For prescribing information, refer to regulatory bodies such as the TGA (Australia), FDA (USA), MHRA (UK), and Medsafe (NZ).
Psoriasis is common among women of reproductive age, with three-quarters of patients developing the disease before their fourth decade. While the condition is lifelong, disease severity can fluctuate.
While psoriasis itself does not present differently in pregnancy, its severity may vary significantly. No pregnancy-specific cutaneous manifestations exist, except in cases of pustular psoriasis of pregnancy, which can be life-threatening and requires systemic therapy.
See Psoriasis for more information.
Treatment selection must balance disease control with fetal safety, as some systemic treatments are teratogenic or have unknown effects in pregnancy.
For most pregnant women, topical treatments and phototherapy provide adequate disease control. In severe cases, systemic therapy may be necessary, requiring multidisciplinary management with dermatology and obstetric teams.
Uncontrolled psoriasis can negatively impact maternal quality of life, increase stress-related complications, and potentially affect pregnancy outcomes. Therefore, a personalised, evidence-based treatment plan is essential.
Topical treatments are the first-line approach in pregnancy. Most are considered safe, but some require caution:
Safe options:
Use with caution:
Avoid:
Narrowband UVB (nUVB) is considered safe and effective for moderate-to-severe psoriasis during pregnancy. However, UVB therapy may deplete folate levels, necessitating folic acid supplementation.
PUVA (psoralen + UVA therapy) possesses a theoretical mutagenic risk; it is recommended to avoid.
For patients with severe or widespread psoriasis requiring systemic therapy, treatment decisions must consider both maternal and fetal risks.
There is increasing evidence supporting the use of biologics during pregnancy for moderate-to-severe psoriasis, particularly when the risk of uncontrolled disease outweighs potential medication risks.
Since many biologics actively cross the placenta in late pregnancy, some clinicians withhold biologic treatment in the last 8–10 weeks of gestation to reduce drug levels in the newborn. This approach must be individualised, as stopping treatment may lead to disease flares.
Biologic-exposed infants may have persistent drug levels at birth, which can interfere with live vaccines such as:
Standard recommendations advise delaying live vaccines until 6–12 months of age if the mother received a biologic beyond the second trimester. In contrast, certolizumab-treated infants may safely receive live vaccines due to minimal drug transfer.
IL-17/IL-23 inhibitors are promising but require more pregnancy-specific research.